METFORMIN — Pharmacology Drug Monograph
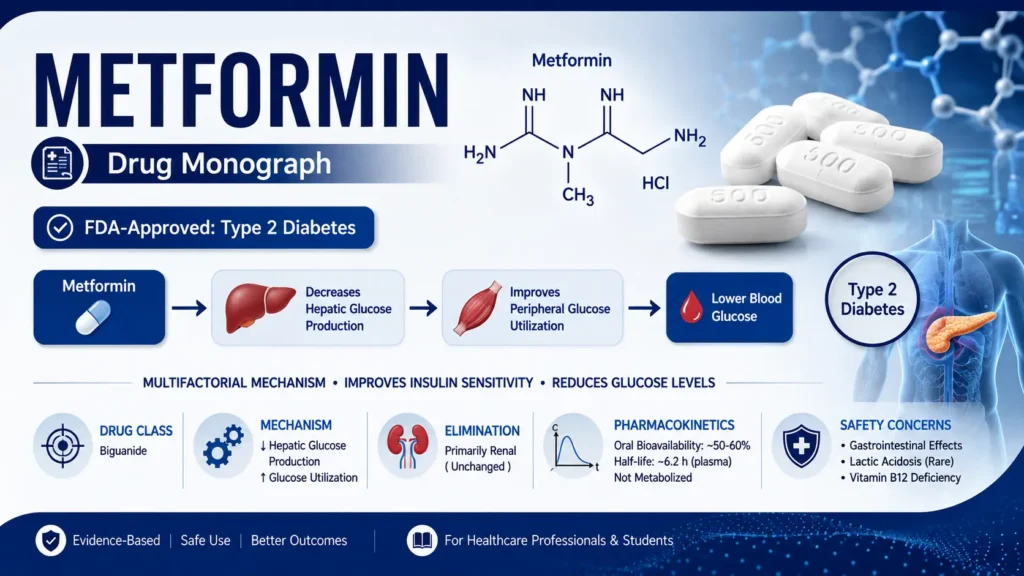
Current metformin pharmacology guide covering FDA-approved uses, mechanism of action, pharmacokinetics, dosage, adverse effects, interactions, monitoring and safety.
What Is Metformin?
Metformin is an oral biguanide antihyperglycemic drug used with diet and exercise to improve glycemic control in people with type 2 diabetes mellitus (T2DM). Current U.S. labeling for several metformin extended-release products includes adults and pediatric patients 10 years and older with T2DM.
Metformin primarily reduces hepatic glucose production and improves glucose utilization. Unlike insulin secretagogues, it does not directly stimulate pancreatic insulin secretion.
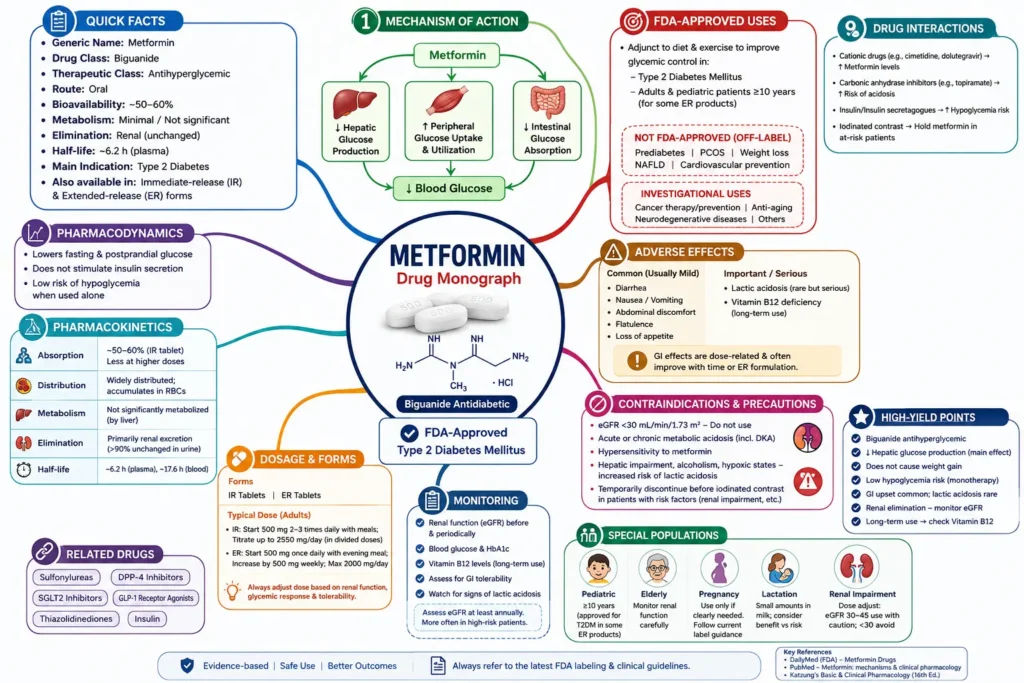
Metformin Quick Facts
| Property | Information |
|---|---|
| Generic name | Metformin |
| Drug class | Biguanide |
| Therapeutic class | Antihyperglycemic |
| FDA-approved use | Type 2 diabetes mellitus |
| Route | Oral |
| Forms | Immediate-release and extended-release products |
| Main effect | ↓ Hepatic glucose production |
| Metabolism | Minimal/no significant hepatic metabolism |
| Elimination | Primarily renal, largely unchanged |
| Common adverse effects | Diarrhea, nausea, vomiting, abdominal discomfort |
| Serious risk | Metformin-associated lactic acidosis |
| Long-term concern | Vitamin B12 deficiency |
| eGFR <30 | Do not use |
FDA-Approved, Off-Label and Investigational Uses
The FDA-approved indication is improvement of glycemic control in type 2 diabetes, as an adjunct to diet and exercise.
| Use | Status |
|---|---|
| Type 2 diabetes | FDA-approved |
| Prediabetes | Not FDA-approved |
| Polycystic ovary syndrome | Not FDA-approved |
| Weight-loss treatment | Not FDA-approved |
| Cancer treatment/prevention | Investigational |
| Anti-aging/longevity | Investigational |
Metformin is being studied for effects beyond diabetes, including cancer, aging, inflammation and neurodegenerative disease, but these research areas should not be presented as established FDA-approved indications. Recent reviews continue to describe these applications as areas of investigation.
Mechanism of Action
Metformin has a multifactorial mechanism of action. Its glucose-lowering effects include:
- Decreased hepatic gluconeogenesis and glucose production
- Increased peripheral glucose utilization
- Improved insulin sensitivity
- Effects on intestinal glucose handling
AMP-activated protein kinase (AMPK) contributes to some metformin effects, but the mechanism is more complex than simple AMPK activation. Recent pharmacology reviews describe AMPK-dependent and AMPK-independent mechanisms involving mitochondrial function, hepatic metabolism, skeletal muscle and intestinal pathways.
High-yield pathway:
Metformin → ↓ hepatic glucose production + ↑ glucose utilization → ↓ blood glucose
Pharmacodynamics
Metformin lowers fasting and postprandial blood glucose without directly increasing insulin secretion. Its overall effect reflects actions in several tissues, particularly the liver, intestine and skeletal muscle.
Because it does not directly stimulate insulin release, metformin has a relatively low intrinsic risk of hypoglycemia when used alone. Hypoglycemia can become more likely when it is combined with insulin or insulin secretagogues.
Pharmacokinetics
Metformin has an oral bioavailability generally reported around 40–60%. It is not significantly metabolized by the liver and is predominantly eliminated through the kidneys. Its elimination is therefore strongly affected by renal function.
The drug has limited plasma protein binding and is eliminated largely unchanged. Renal impairment can increase metformin exposure and prolong elimination.
Dosage and Formulations
Metformin is available in immediate-release and extended-release oral formulations.
For one current extended-release U.S. label, the recommended starting dose is 500 mg once daily with the evening meal, increased by 500 mg weekly according to response and tolerability, up to 2,000 mg once daily. Tablets should be swallowed whole.
Immediate-release products have different dosing schedules and may have a labeled maximum total daily dose of 2,550 mg. Product-specific prescribing information should always be checked before clinical use.
Renal Function and Contraindications
Renal function is particularly important because metformin is substantially eliminated by the kidneys.
- eGFR ≥45: Treatment may generally be continued according to labeling and clinical circumstances.
- eGFR 30–45: Initiation is not recommended; continuation requires benefit-risk assessment.
- eGFR <30: Metformin should not be used.
Major contraindications include severe renal impairment, metabolic acidosis including diabetic ketoacidosis, and hypersensitivity to metformin.
Adverse Effects
The most common adverse effects are gastrointestinal:
- Diarrhea
- Nausea
- Vomiting
- Flatulence
- Abdominal discomfort
Long-term therapy can be associated with vitamin B12 deficiency, making B12 assessment relevant when clinically indicated.
The most serious recognized toxicity is metformin-associated lactic acidosis, a rare but potentially life-threatening condition. Risk increases particularly with significant renal impairment and other conditions that promote metformin accumulation or impaired lactate handling.
Drug Interactions
Important interaction considerations include:
- Cationic drugs: Some renally eliminated cationic medicines can increase metformin exposure.
- Carbonic anhydrase inhibitors: May increase the risk of metabolic acidosis.
- Insulin/insulin secretagogues: May increase hypoglycemia risk.
- Iodinated contrast: Metformin may need to be temporarily discontinued in specified patients and procedures.
Current U.S. labeling specifically recommends attention to renal function around iodinated contrast procedures.
Monitoring
Key monitoring parameters include:
- eGFR/renal function
- Blood glucose
- HbA1c
- Vitamin B12 when appropriate
- Gastrointestinal tolerability
- Clinical factors associated with lactic acidosis
For patients taking metformin, current labeling recommends obtaining eGFR before treatment and at least annually, with more frequent assessment in patients at increased risk of renal impairment.
Special Populations
Children: Certain U.S. formulations are approved for patients aged 10 years and older with T2DM.
Older adults: Renal function requires particular attention because kidney function may decline with age.
Renal impairment: Reduced kidney function substantially affects metformin clearance and safety.
Pregnancy and lactation: Use should be evaluated using current product labeling and individualized clinical assessment.
Clinical Evidence and Current Research
Metformin has decades of clinical evidence supporting its glucose-lowering efficacy in T2DM. Current research continues to examine its molecular effects on mitochondrial metabolism, intestinal signaling, glucose disposal and other metabolic pathways. A 2026 review emphasizes that metformin’s pharmacology involves multiple tissue-specific mechanisms rather than a single molecular target.
Recent experimental research has also identified intestinal mitochondrial complex I inhibition as a potential contributor to metformin’s glucose-lowering effects, demonstrating how understanding of this established drug continues to evolve.
Regulatory Status
Metformin remains an FDA-approved oral antihyperglycemic medicine for type 2 diabetes mellitus. Current U.S. labeling was updated for some extended-release products in 2026, including indications and dosing information.
Because multiple manufacturers and formulations exist, researchers and healthcare professionals should consult the specific current product label rather than assuming that all metformin products have identical labeling.
High-Yield Student Points
- Class: Biguanide
- Main indication: Type 2 diabetes
- Main action: ↓ hepatic glucose production
- Mechanism: Multifactorial; AMPK is involved but is not the complete explanation
- Elimination: Mainly renal
- Common ADRs: GI disturbances
- Serious toxicity: Lactic acidosis
- Long-term concern: Vitamin B12 deficiency
- eGFR <30: Do not use
- eGFR 30–45: Do not initiate
- Hypoglycemia: Low intrinsic risk as monotherapy
FAQs
Is metformin FDA-approved for weight loss?
No. Weight loss is not an FDA-approved indication for metformin.
Is metformin FDA-approved for PCOS?
No. PCOS is not an FDA-approved indication in the United States.
What is the main mechanism of metformin?
It primarily reduces hepatic glucose production and improves peripheral glucose utilization and insulin sensitivity.
Is metformin metabolized by the liver?
Metformin undergoes little to no significant hepatic metabolism and is primarily eliminated by the kidneys.
What is the most important safety issue?
Metformin-associated lactic acidosis is the major serious safety concern, particularly in patients with significant renal impairment.
Related Drugs
- Sulfonylureas
- DPP-4 inhibitors
- SGLT2 inhibitors
- GLP-1 receptor agonists
- Thiazolidinediones
- Insulin
- Other antihyperglycemic drugs